



On July 27th, MapLight Therapeutics released topline* results from ZEPHYR, a Phase 2 trial testing a new schizophrenia medication called ML-007C-MA. The trial met its primary endpoint, and the twice-daily dose improved psychotic symptoms compared with placebo. The more interesting result, at least for me, was the prespecified cognitive endpoint. In a subset of patients with cognitive impairment, performance improved with treatment, and the size of that improvement was in the same range as what had previously been reported with KarXT.
I have argued in previous pieces that schizophrenia is a much broader illness than psychosis. Hallucinations and delusions often bring someone into a hospital and are the symptoms traditional antipsychotic medications treat most reliably. Cognitive and negative symptoms tend to determine whether that person returns to school, holds a job, maintains relationships and lives independently.
Traditional antipsychotic medications are thought to act via blocking of dopamine D2 receptors. KarXT, now marketed as Cobenfy, was historically important because it was the first muscarinic agent to be approved for treatment of adults with schizophrenia. More specifically, KarXT is thought to activate the M1 and M4 subtypes of muscarinic receptors in the brain, which are thought to impact all symptom domains in schizophrenia. The ZEPHYR result now provides another opportunity to ask whether this class may indeed have such broad efficacy.
There is also a commercial question, which is whether MapLight has produced a better version of KarXT. MapLight’s investor presentation encourages that comparison by placing ZEPHYR beside KarXT’s Phase 3 trials and emphasizing differences in tolerability, fasting requirements and titration. A phase-matched comparison gives a more accurate picture. When ZEPHYR is placed beside KarXT’s original Phase 2 trial, KarXT produces a larger antipsychotic effect and a more favorable adverse-event profile. The current evidence therefore gives KarXT the stronger overall clinical position, while the cognitive result from ZEPHYR strengthens the scientific case for the broader M1/M4 approach.
What Happened in ZEPHYR
For families following the development of a new schizophrenia medication, the practical questions usually concern the size of the clinical improvement, the kinds of symptoms that changed and the likelihood that patients will remain on the drug over time. ZEPHYR offers encouraging information in each area, along with several reasons for restraint.
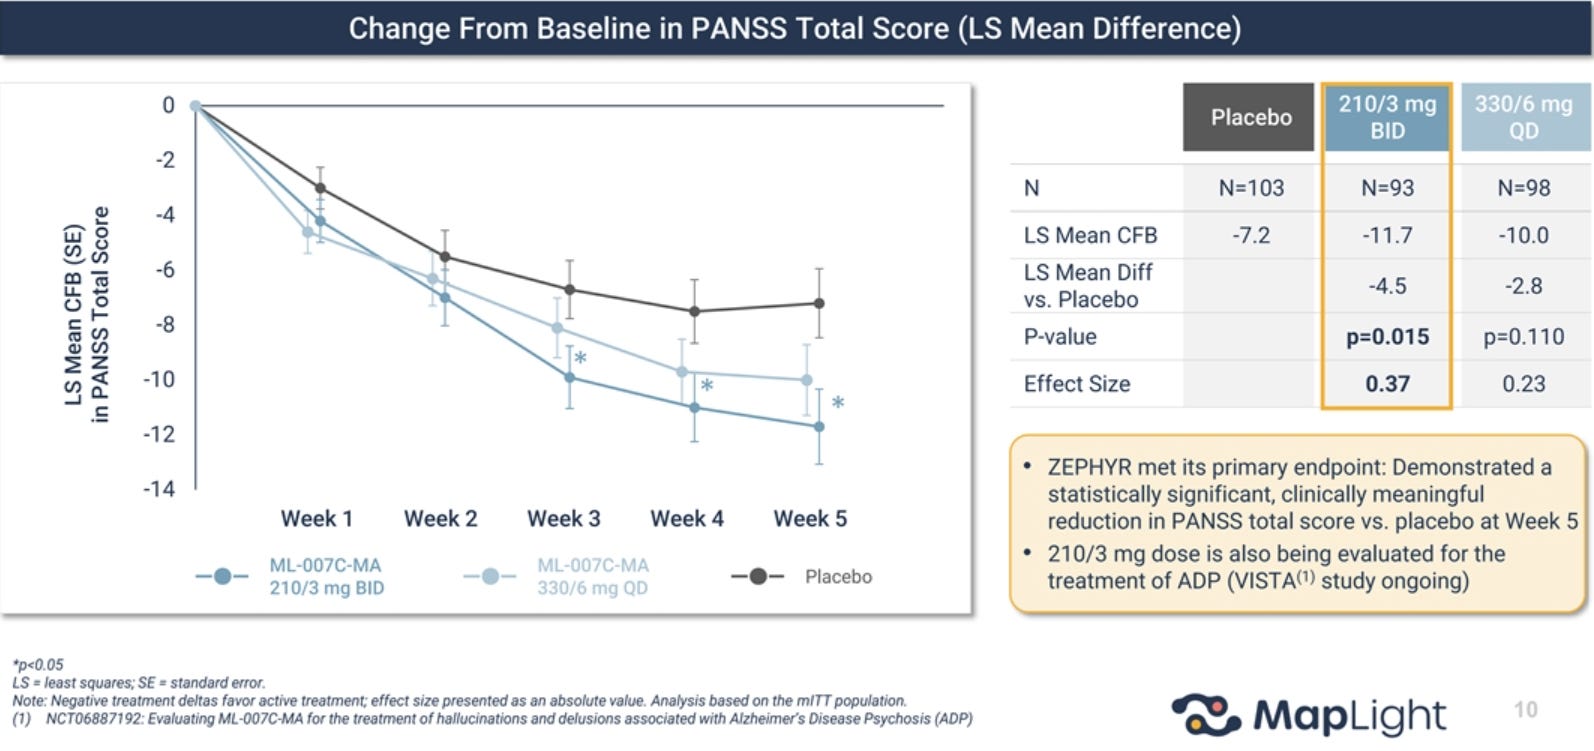
The trial enrolled 307 adults with an acute exacerbation of schizophrenia and assigned them to placebo, ML-007C-MA 210/3 mg twice daily, or ML-007C-MA 330/6 mg once daily. After five weeks, the twice-daily dose produced a statistically significant improvement over placebo on the Positive and Negative Syndrome Scale, or PANSS, which is the standard symptom rating scale used in acute schizophrenia trials. The once-daily arm produced a smaller numerical improvement that remained below the prespecified statistical threshold.
The dosing result has practical implications. Once-daily medications are generally easier to incorporate into ordinary life, particularly for people whose illness already affects organization, memory and routine. Whichever regimen MapLight ultimately advances, the regimen actually supported by ZEPHYR’s data is the twice-daily one.
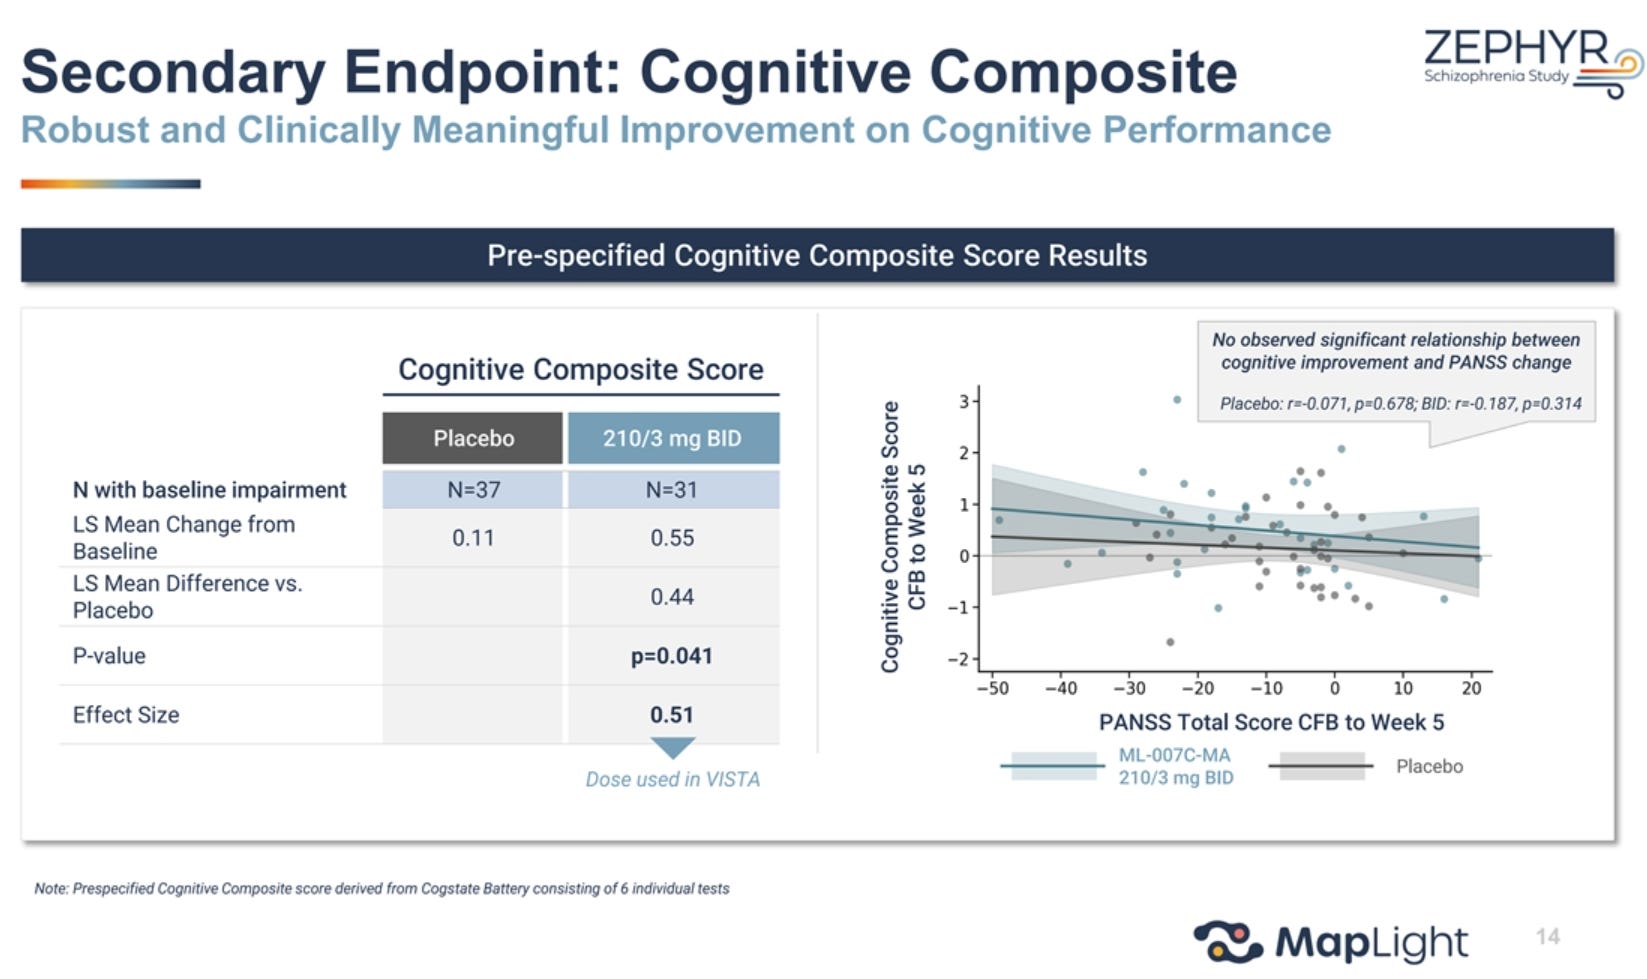
Now, let’s turn to the cognitive finding. A large proportion of people with schizophrenia have difficulties with attention, processing speed, working memory and the organization of thought. These difficulties are strongly associated with long-term functional outcomes. In ZEPHYR, participants who began the study with measurable cognitive impairment improved on a cognitive battery when treated with the twice-daily dose. The degree of cognitive improvement showed little relationship to the degree of improvement in their psychotic symptoms, which supports the possibility that M1/M4 agonists improve cognition in psychotic disorders independent of psychosis itself.
A reproducible cognitive benefit from two different muscarinic agents is potentially a big deal.
For readers who want the underlying numbers: ZEPHYR enrolled 307 participants across 25 U.S. sites, randomized 1:1:1 to placebo, ML-007C-MA 210/3 mg twice daily, or ML-007C-MA 330/6 mg once daily over a five-week blinded treatment period. On the primary endpoint, change in PANSS Total Score at Week 5, the twice-daily arm produced an effect size of 0.37 in the modified intent-to-treat analysis, corresponding to a 4.5-point advantage over placebo with p=0.015. The prespecified completer analysis yielded an effect size of 0.50 and a 6.0-point difference with p=0.002. The once-daily arm produced an effect size of 0.23 with p=0.110. Secondary measures in the twice-daily arm included an effect size of 0.48 on the Clinical Global Impression of Severity and 0.39 on the PANSS positive-symptom Marder factor. Among participants with baseline cognitive impairment, the Cogstate composite yielded an effect size of 0.51 with p=0.041. Cognitive change and PANSS change were uncorrelated in the active arm, r=-0.187 with p=0.314. Serious or drug-related severe adverse events were absent, gastrointestinal adverse events led to discontinuation in 2.0 percent of participants receiving the twice-daily dose, and the trial showed no clear metabolic, hepatic, urinary-retention or movement-related signal. The formulation also carries no fasting requirement.
The Muscarinics
KarXT was approved in September 2024 and became the first antipsychotic in more than seventy years whose primary mechanism does not involve direct dopamine D2 receptor blockade. It was the first muscarinic.
The development history of other muscarinic drugs has raised the question of whether both M1 and M4 activation is needed for clinical efficacy. Emraclidine, an M4-selective positive allosteric modulator, produced promising early results and then missed the primary endpoint in two Phase 2 trials. Direclidine, an M4-selective agonist, produced a statistically significant effect at the lowest of four doses in its Phase 2 study, with progressively less convincing results at the higher doses (strange, huh?). Like KarXT, ML-007C-MA is a dual M1/M4 agonist, and that appears to have worked!
Several interpretations remain possible. Dual M1/M4 activation may provide a more reliable antipsychotic profile than M4-selective approaches. M1 activity may contribute primarily to cognition while M4 accounts for more of the effect on psychosis. The dose-response properties of these receptors may also be unusually sensitive to exposure, timing and receptor desensitization, which could help explain the U-shaped result with direclidine and the separation between MapLight’s two regimens. A small number of trials leaves considerable uncertainty around each explanation.
The accumulating data still point toward a meaningful distinction between M1/M4 agonism and M4-selective strategies. KarXT has produced positive results across three acute trials. ML-007C-MA has now produced a positive Phase 2 result. Both compounds have also generated cognitive signals in participants who began treatment with cognitive impairment. Emraclidine failed in two Phase 2 trials, while direclidine’s result was concentrated at one dose. This pattern gives the dual-agonist hypothesis increasing plausibility, even though the separate contributions of the two receptors remain unresolved.
For readers who want more mechanistic detail: M4 receptors are expressed prominently in striatal circuits that regulate dopamine release, providing an indirect path toward control of psychotic symptoms. M1 receptors are heavily expressed in prefrontal networks, potentially impacting negative and cognitive symptoms. KarXT and ML-007C-MA stimulate both receptor types in the brain while pairing the central agonist with a peripherally acting anticholinergic intended to limit gastrointestinal and other peripheral cholinergic effects. Emraclidine modulates M4 selectively, and direclidine is an M4-selective agonist. AbbVie’s two EMPOWER trials of emraclidine missed their primary endpoints in November 2024. Direclidine’s Phase 2 trial tested four doses and produced statistical significance at the lowest dose, creating a U-shaped dose-response pattern. The field currently has evidence for multiple pharmacological routes into the muscarinic system, along with a limited ability to determine which receptor profile and exposure pattern will prove most reliable.
A Virtual Comparison With KarXT
Any comparison between ML-007C-MA and KarXT is necessarily indirect. The drugs have never been tested against one another in the same trial, and differences in patients, sites, placebo response, analytical decisions and study conduct can influence the apparent size of an effect. Cross-trial comparisons are still informative when studies are aligned as closely as possible.
MapLight’s presentation compares ZEPHYR with KarXT’s Phase 3 program, where the effect sizes were smaller than in KarXT’s original Phase 2 study and the rate of treatment-emergent adverse events was higher. This makes ML-007C-MA appear closer to KarXT on efficacy and more favorable on tolerability. The more comparable study is EMERGENT-1, KarXT’s five-week Phase 2 trial in 182 hospitalized patients with acute schizophrenia.
The efficacy difference is substantial. The twice-daily dose of ML-007C-MA produced an effect size of 0.37 in the primary modified intent-to-treat analysis. EMERGENT-1 produced an effect size reported as 0.75 in the trial’s original description and as 0.81 in a later pooled reanalysis, roughly double to more than double ZEPHYR’s number depending on which figure is used. KarXT’s effect subsequently settled at 0.61 and 0.60 in its two Phase 3 trials, with a pooled effect size of 0.65 across all three studies (Kaul et al., 2024).
Early clinical trials often generate larger estimates than later confirmatory studies, particularly when the sample is modest and the placebo response happens to be favorable, a pattern sometimes called the winner’s curse. KarXT followed that familiar trajectory, shrinking from roughly 0.75 to 0.81 in Phase 2 down to roughly 0.60 to 0.65 by the time its Phase 3 program was complete. ZEPHYR begins from a more modest estimate than KarXT’s own Phase 2 result, and if MapLight’s drug follows a similar trajectory, a future confirmatory trial is arguably more likely to land below 0.37. A successful Phase 3 program could still confirm a clinically useful antipsychotic effect, but the current data provide little basis for describing ML-007C-MA as more efficacious than KarXT.
Tolerability also looks different after phase matching. In EMERGENT-1, 53.9 percent of participants receiving KarXT and 43.3 percent receiving placebo reported a treatment-emergent adverse event, giving an active-placebo difference of approximately eleven percentage points. In ZEPHYR, those rates were 74.7 percent for the twice-daily ML-007C-MA arm and 48.1 percent for placebo, a difference of approximately twenty-seven percentage points, roughly two and a half times as large. Adverse events led to discontinuation in 3.3 percent of participants receiving KarXT in EMERGENT-1 and 7.1 percent receiving the twice-daily dose of ML-007C-MA in ZEPHYR (Correll et al., 2022).
These comparisons deserve the same caution as the efficacy comparison. Adverse-event collection and classification can vary among trials, and the severity and clinical consequences of the events may carry more practical meaning than the raw percentage of patients reporting any event. Most adverse events in both studies were mild or moderate and reflected the expected cholinergic effects of the drugs. ML-007C-MA also offers potential practical advantages through its lack of a fasting requirement and simpler titration.
The overall picture still favors KarXT on the evidence available today. It produced a larger effect at the same stage of development, maintained a clinically meaningful effect through two Phase 3 trials, and had a more favorable phase-matched adverse-event profile. ML-007C-MA has demonstrated enough efficacy to justify further development, and its eventual position will depend on whether the ZEPHYR result replicates in a confirmatory trial and whether its practical formulation advantages translate into better persistence in ordinary clinical use.
The Cognitive Signal Has Now Been Replicated
In 2022, researchers published a post hoc analysis of cognitive testing from EMERGENT-1 (Sauder et al., 2022). KarXT had little detectable cognitive effect across the full trial population, which included patients spanning a wide range of baseline performance. Among the participants who entered the study with clinically meaningful cognitive impairment, KarXT produced a moderate improvement compared with placebo. That improvement showed little relationship to the change in psychotic symptoms.
The result initially carried the familiar limitations of a post hoc subgroup analysis. The subgroup was small, the threshold for impairment was applied after the main trial had been completed, and participants selected for low baseline scores tend to improve partly through regression toward the mean. A later pooled analysis across the EMERGENT trials used a broader battery and a larger sample and found a comparable effect size of 0.54 (Horan et al., 2025).
ZEPHYR now extends the finding across molecules. MapLight prespecified cognitive performance as a secondary endpoint in participants with baseline cognitive impairment. The twice-daily dose produced an effect size of 0.51, close to the original KarXT estimate of 0.50 and the later pooled estimate of 0.54. Cognitive improvement again showed little association with improvement in psychotic symptoms.
The convergence is striking. KarXT produced the signal in an exploratory Phase 2 analysis and then reproduced a similar effect in pooled trial data using a broader battery. ML-007C-MA produced almost the same effect size in a prespecified analysis of a different Phase 2 trial. That two independent teams, years apart, converged on such a similar number makes the muscarinic-cognition link highly plausible.
From Drug Response to Precision Psychiatry
There is another way to interpret these results that connects to the problem of precision psychiatry.
Cognitive impairment by itself remains a broad feature. Two patients can receive similarly low composite scores for very different reasons. Only tasks amenable to computational dissection would be capable of revealing the underlying impairments.
This is where the drug-development and measurement problems begin to converge. Future trials could use tasks designed to separate these cognitive processes and determine which component changes with treatment. A reliable association between a particular computational parameter and response to an M1/M4 agonist would move the field closer to a treatment-relevant axis, with the medication serving as both an intervention and a probe of the illness structure.
The replicated cognitive signal is still several steps away from that standard. Nonetheless, its replication across KarXT and ML-007C-MA gives the field a stronger starting point for prospective stratification.
Reading the Market Reaction
MapLight’s stock closed roughly seventy percent lower on the day of the ZEPHYR announcement. The reaction makes sense from the perspective of investors who had expected a clearly differentiated successor to KarXT. The once-daily regimen missed the primary endpoint, the effective twice-daily regimen produced a smaller PANSS effect than KarXT’s own Phase 2 trial, and the gastrointestinal adverse-event burden remained substantial. Each of these weakens the case for an obvious best-in-class commercial profile.
The scientific interpretation can be more favorable without ignoring those concerns. Positive trials remain relatively rare in schizophrenia drug development, and ML-007C-MA produced a coherent effect across PANSS, CGI-S and positive symptoms, alongside a cognitive result that had already appeared with another dual M1/M4 agonist. Investors and scientists were, in effect, reading two different documents. One was pricing the probability that ML-007C-MA competes commercially with an approved product. The other was asking what the trial reveals about muscarinic biology and the possibility of reaching symptom domains that dopamine-blocking medications have served poorly.
Several analysts maintained favorable ratings after reducing their price targets, which is consistent with a reset in commercial expectations rather than abandonment of the program. MapLight still has a path into a confirmatory pivotal trial, along with the possibility of testing alternate once-daily regimens later. The cognitive signal may also have relevance to the company’s ongoing program in Alzheimer’s disease psychosis, where preservation of cognition carries obvious importance.
The Dawn of the Muscarinics
When Cobenfy first worked in a patient of mine,
The Cobenfy Advance: Early Clinical Experience with Schizophrenia's First Breakthrough in Decades

Three weeks into treatment with Cobenfy, Tim looked me in the eyes for the first time.
I described it as a light bulb turning on. The empty, thousand-yard stare that psychosis leaves on a face lifted within weeks, replaced by someone visibly present again. At the time, that was a single clinician’s observation, vivid but impossible to generalize from. It could have been xanomeline-trospium specifically, some quirk of that molecule, that patient, that moment. ZEPHYR may have changed that. A second company, working from a different molecule built around the same receptors, has now produced a coherent antipsychotic effect and a cognitive signal that lands almost exactly where KarXT’s did. Does it also produce a lightbulb effect or what clinicians are now calling “the cobenfy clearing”? I don’t know, and time will tell.
But even if it did, we should not think that this means the muscarinic drugs available today solve schizophrenia. They do not work for everyone. Yet, something foundational is happening. For seventy years, psychiatry had exactly one lever for psychosis: block dopamine, and vary the side effects. There are now, demonstrably, at least two levers that work, built independently by different people. That is what a watershed looks like in this field: the moment a mechanism stops depending on whether a single company’s molecule happens to be good, and starts existing as a category clinicians can build on. The muscarinics are here to stay. What they will ultimately be able to do for patients is being written.
*Topline results are the initial, high-level summary of a trial’s main findings that a company puts out within days of a trial ending, well before the full dataset is published and reviewed by outside scientists.
If you found this piece useful, please consider subscribing and sharing it with someone who might find it clarifying. Paid subscriptions help support the time required to produce this work.